Author: admin

  • WMCHealth Is Replacing 88 Applications With Epic. The Hardest Part May Be Replacing 88 Sets of Habits.

    WMCHealth Is Replacing 88 Applications With Epic. The Hardest Part May Be Replacing 88 Sets of Habits.

    Most EHR implementations are described as software projects.

    Westchester Medical Center Health Network is showing why that description no longer goes far enough.

    WMCHealth is implementing Epic across its network, but the project is expected to do much more than replace an electronic health record. By the time the transformation is complete, the health system expects Epic to displace 88 separate applications that accumulated across the organization over years of growth.

    That means WMCHealth is not simply asking clinicians and employees to learn Epic.

    It is asking thousands of people to unlearn dozens of systems, screens, shortcuts, workflows and habits that have become part of how they work.

    And that may be the harder transformation.

    Becker’s Hospital Review reports that WMCHealth currently operates a fragmented technology environment across its nine-hospital network. Some facilities use Oracle Health, formerly Cerner. Others use Altera’s Paragon platform, formerly Allscripts, while another smaller system supports a skilled nursing facility. WMCHealth plans to replace much of that fragmented environment with a single enterprise Epic implementation.

    The go-live is scheduled for December 4, 2027.

    The technology transition will happen on a defined date.

    The behavioral transition will take much longer.

    88 Applications Means 88 Sources of Institutional Muscle Memory

    There is an understandable financial argument for application consolidation.

    Every additional application can bring licensing costs, infrastructure requirements, interfaces, security responsibilities, maintenance, vendor relationships and support requirements.

    Multiply those costs across dozens of applications and consolidation begins to make enormous financial sense.

    WMCHealth CIO Leo Bodden told Becker’s that once the Epic implementation is complete and the legacy applications are retired, the health system expects its costs to be significantly lower than what it currently spends supporting its existing environment.

    But there is another form of technical debt that does not appear neatly on an IT balance sheet.

    Human workflow debt.

    Every application being retired has users who know how to operate it.

    Some of those users may have spent years developing expertise.

    They know where information lives.

    They know the sequence of clicks.

    They know the strange workaround required for an unusual situation.

    They know which screen opens next.

    They know what happens when something goes wrong.

    That knowledge becomes automatic.

    When the application disappears, much of that muscle memory becomes useless overnight.

    A successful consolidation strategy therefore has to retire two things simultaneously:

    The old software.

    And the old way of working.

    WMCHealth Is Preparing for a True Big-Bang Transformation

    WMCHealth’s own Epic implementation planning documents show the scale of what is coming.

    The health system has said Epic will operate as a single enterprise instance and that the implementation is planned as a big-bang go-live, with all facilities included in scope. Specialty areas under consideration include major clinical environments such as laboratory, pharmacy, operating room, anesthesia, oncology, radiology, cardiology and behavioral health functionality.

    A big-bang implementation creates one enormous advantage.

    Everyone moves together.

    It can eliminate years of maintaining parallel environments while different facilities wait for their turn.

    But it also concentrates risk.

    Instead of one department learning a new workflow, many departments are learning simultaneously.

    Instead of one facility needing support, the entire enterprise may need support.

    Emergency departments.

    Inpatient nursing.

    Ambulatory clinics.

    Operating rooms.

    Pharmacies.

    Laboratories.

    Radiology.

    Cardiology.

    Registration.

    Scheduling.

    Revenue cycle.

    Health information management.

    Every one of those environments contains dozens, sometimes hundreds, of workflows.

    And every workflow eventually reaches the same question:

    Does the user know what to do next?

    Application Consolidation Creates a Training Problem That IT Architecture Diagrams Do Not Show

    Imagine a physician who has practiced at one WMCHealth hospital for several years.

    That physician knows the existing EHR well.

    Then Epic arrives.

    The clinical knowledge has not changed.

    The patient still requires the same care.

    But the digital pathway for performing that care may be completely different.

    Where is the order?

    Where is the result?

    How do I modify it?

    Where are messages?

    How do I complete the note?

    How do I review medication history?

    Where do I find outside records?

    How is discharge handled?

    Now multiply that experience across thousands of employees.

    Then multiply it again across dozens of applications being eliminated.

    This is why EHR consolidation cannot be treated simply as a technology simplification initiative.

    From the user’s perspective, consolidation may initially feel like increased complexity.

    IT sees fewer applications.

    The clinician sees an unfamiliar system.

    The CIO sees application rationalization.

    The nurse sees a workflow that used to take three familiar steps and now requires learning a new sequence.

    Both views can be correct.

    The organization only realizes the benefits when the second problem is solved.

    One EHR Can Create Consistency, but Only if People Use It Consistently

    The strategic value of an enterprise EHR is significant.

    A unified environment can reduce fragmentation.

    Patient information can move more easily across facilities.

    Clinicians can operate from a shared record.

    Organizations can standardize workflows.

    Training can become more consistent.

    Analytics can become easier.

    Security can become easier to manage.

    Application support can become less fragmented.

    WMCHealth has already been pursuing greater organizational integration beyond technology. In July 2026, the system announced that eight of its hospitals had been unified under a single hospital license, a change intended to improve coordination and allow the network to operate more cohesively.

    Epic fits naturally into that broader strategy.

    But putting everyone on one platform does not automatically mean everyone uses the platform in the same way.

    Local habits can survive technology consolidation.

    A department may create a workaround.

    A clinician may continue using an inefficient sequence because it feels familiar.

    One location may develop unofficial instructions.

    Another may interpret the workflow differently.

    Screenshots get circulated.

    Tip sheets become outdated.

    Experienced employees teach new employees the way they learned, even after the workflow changes.

    Before long, one standardized EHR can contain multiple unofficial ways of working.

    That is why workflow governance matters just as much as application governance.

    Go-Live Support Becomes More Important When Systems Are Consolidated

    During a major EHR implementation, mistakes are sometimes framed as training problems.

    That is too simplistic.

    No realistic training program can prepare every user for every situation they will encounter in a live clinical environment.

    Users can be prepared for common workflows.

    They can practice.

    They can complete simulations.

    They can receive role-based training.

    But real healthcare does not happen according to a training script.

    A patient does something unexpected.

    A clinician encounters a workflow they only perform twice a year.

    A nurse floats into another department.

    A physician covering another service encounters a specialty workflow.

    A new employee arrives after the original training sessions have ended.

    This is why large implementations depend heavily on support after training.

    At-the-elbow personnel.

    Super users.

    Command centers.

    Analysts.

    Trainers.

    Application teams.

    Service desks.

    All of these resources help close the gap between classroom readiness and real-world proficiency.

    For WMCHealth, that gap could become particularly important because the organization is moving from multiple legacy environments into a single enterprise platform.

    The question is not simply whether employees understand Epic.

    It is whether they can translate everything they previously did across dozens of applications into the correct new workflow.

    The Most Valuable Go-Live Questions Are Often the Simplest

    During go-live, support teams hear questions that may appear basic:

    “Where is this?”

    “How do I document this?”

    “How do I change this order?”

    “Where did this information move?”

    “How do I complete this workflow now?”

    Those questions are not evidence that clinicians lack expertise.

    A cardiovascular surgeon does not become less capable because the location of an Epic activity is unfamiliar.

    An experienced nurse does not lose clinical judgment because a documentation workflow has changed.

    A pharmacist does not forget pharmacy practice because medication functionality appears differently.

    They are adapting clinical expertise to a new digital environment.

    The faster that adaptation occurs, the sooner the organization begins realizing the value of the EHR investment.

    That is why workflow guidance matters.

    Every Retired Application Creates an Opportunity to Simplify

    There is another side to WMCHealth’s transition.

    Replacing 88 applications is not merely disruptive.

    It is an opportunity.

    Health systems accumulate software for understandable reasons.

    A new department needs functionality.

    An acquired hospital brings an existing platform.

    A specialty purchases a point solution.

    A temporary solution becomes permanent.

    Years pass.

    Eventually users are logging into multiple systems simply to complete one episode of work.

    Information gets copied between applications.

    Passwords multiply.

    Interfaces have to be maintained.

    Employees must remember which application contains which information.

    That environment creates cognitive burden.

    A successful Epic consolidation could remove a significant amount of that fragmentation.

    But there is an important condition.

    The new workflow must actually be simpler.

    Replacing five applications with one system has little value if employees require extensive manual workarounds inside the replacement.

    Application rationalization should therefore be paired with workflow rationalization.

    Organizations should not merely ask:

    “What software can Epic replace?”

    They should also ask:

    “What unnecessary steps can disappear when that software is replaced?”

    That is where technology transformation begins producing operational transformation.

    WMCHealth Is Also Changing More Than the EHR

    The complexity becomes even more striking because Epic is not WMCHealth’s only major transformation initiative.

    Becker’s reports that WMCHealth is also undertaking a systemwide Workday enterprise resource planning rollout affecting finance, human resources and supply chain operations.

    WMCHealth’s own workforce-management planning documents acknowledge the challenge of simultaneous transformation. The organization describes coordinated change management across Workday, workforce management and EHR initiatives, including stakeholder engagement, communications, role-based training and adoption planning. The documents specifically reference managing change saturation across the organization.

    That phrase deserves attention.

    Change saturation.

    Healthcare workers already operate in high-pressure environments.

    When multiple enterprise platforms change within a relatively short period, employees are not simply learning one new tool.

    They are learning a new digital workplace.

    That makes accessible, continuous guidance far more important.

    What Happens Six Months After Go-Live?

    Implementation plans naturally concentrate attention on the launch.

    But a different question may matter more:

    What happens in June 2028?

    By then, the consultants may be gone.

    Temporary command-center staffing may be reduced.

    At-the-elbow resources may have moved to another project.

    But employees will still have questions.

    New employees will need onboarding.

    Existing employees will encounter unfamiliar workflows.

    Epic upgrades will introduce changes.

    Departments will optimize processes.

    New functionality may be activated.

    Artificial intelligence tools may alter documentation and information retrieval.

    The EHR will continue evolving.

    Healthcare organizations therefore need to think beyond go-live support and toward continuous EHR enablement.

    Support cannot disappear simply because the implementation project has been declared complete.

    This Is the Problem GoLiveX Is Built Around

    GoLiveX approaches EHR support from a simple premise:

    Healthcare professionals should be able to get workflow guidance when they need it, not only when a trainer happens to be standing nearby.

    GoLiveX provides AI-powered guidance for major EHR platforms including Epic, Oracle Health/Cerner and MEDITECH.

    That becomes particularly relevant in consolidation projects.

    Before an Epic transition, one organization may contain employees familiar with Cerner.

    Others may come from Allscripts or Paragon environments.

    Others may know MEDITECH.

    New employees may have Epic experience from a previous hospital but still need to understand how the current organization has configured its workflows.

    The platform name alone does not answer the question.

    Users need practical guidance about what they are trying to accomplish.

    GoLiveX is designed to support that workflow-learning layer without requiring protected health information.

    It is not intended to replace formal training, super users, analysts or at-the-elbow teams.

    It can extend their reach.

    During go-live, it can provide another path to an answer.

    After go-live, it can help preserve access to workflow knowledge when temporary implementation resources are no longer available.

    And during optimization, it can help users adapt as workflows continue changing.

    The Real ROI of Application Consolidation Depends on the User

    WMCHealth expects meaningful financial benefits from retiring applications and simplifying its technology environment.

    That makes sense.

    Fewer systems can mean fewer contracts.

    Fewer interfaces.

    Less infrastructure.

    Reduced technical debt.

    Simplified support.

    More consistent data.

    But the real return on investment ultimately has another dependency:

    Can employees use the new environment efficiently?

    If users struggle, create workarounds or require extensive manual intervention, part of the expected benefit disappears.

    If clinicians become proficient quickly, standardized technology can translate into standardized operations.

    That is why adoption should not be treated as the soft side of an EHR implementation.

    It is part of the financial model.

    December 4, 2027 Will Be the Beginning, Not the End

    WMCHealth’s Epic project began in April 2026 and is expected to culminate in a December 4, 2027 big-bang launch. Becker’s reports that the organization expects to eliminate much of the technical debt accumulated across its hospitals once the implementation and application retirement process is complete.

    That will be an enormous milestone.

    But the most interesting question begins afterward.

    Can a health system that once operated multiple EHRs and dozens of applications create a genuinely unified clinical technology environment?

    Can thousands of employees move from familiar local workflows to standardized enterprise processes?

    Can the organization make the transition easier rather than merely different?

    Can workflow knowledge remain available after the implementation teams leave?

    WMCHealth is replacing 88 applications.

    That is the technology story.

    The bigger story is replacing thousands of ingrained digital habits with better ones.

    And that is why the success of modern EHR consolidation will increasingly depend not only on the platform hospitals choose, but on how effectively they help people use it.

    About GoLiveX

    GoLiveX is an AI-powered EHR workflow guidance platform designed to help healthcare professionals navigate Epic, Oracle Health/Cerner, MEDITECH and other clinical systems. GoLiveX provides on-demand workflow guidance without requiring protected health information, helping clinicians, trainers and healthcare IT teams during implementation, go-live, stabilization, optimization and everyday EHR use.


    SEO Publishing Block

    Recommended SEO Title:
    WMCHealth Is Replacing 88 Applications With Epic: The Hidden EHR Adoption Challenge

    URL Slug:
    wmchealth-epic-implementation-88-applications-ehr-adoption

    Primary / Focus Keyword:
    Epic EHR implementation

    Secondary / Related Keywords:
    WMCHealth Epic, Epic go-live, Epic implementation support, EHR consolidation, application consolidation healthcare, EHR workflow training, Epic training, EHR adoption, clinical workflow support, at-the-elbow support, healthcare IT transformation, EHR optimization, legacy EHR migration, Cerner to Epic migration, Allscripts to Epic, enterprise EHR implementation

    Meta Description:
    WMCHealth plans to replace 88 applications with a single Epic environment. The consolidation shows why workflow adoption, training and continuous EHR support are critical to realizing the benefits of a major EHR transformation.

    Recommended Category:
    EHR Implementation & Go-Live

    Suggested Tags:
    Epic, WMCHealth, EHR Consolidation, EHR Go-Live, Healthcare IT, EHR Training, Application Rationalization, Clinical Workflows, EHR Optimization, GoLiveX

    Suggested Social Headline:
    WMCHealth Is Replacing 88 Apps With Epic. Replacing the Software May Be Easier Than Replacing the Habits.

    Source Story:
    Becker’s Hospital Review, “Epic is about to retire 88 applications at WMCHealth,” published September 18, 2026. WMCHealth expects the implementation to consolidate its fragmented EHR environment and eliminate 88 applications, with a big-bang Epic go-live planned for December 4, 2027.


  • 34 More HCA Hospitals Just Went Live on MEDITECH Expanse. The Real Challenge Is Making 34 Hospitals Work Like One.

    34 More HCA Hospitals Just Went Live on MEDITECH Expanse. The Real Challenge Is Making 34 Hospitals Work Like One.

    Thirty-four hospitals.

    Multiple states.

    Thousands of clinicians.

    Different departments, specialties, workflows, operational histories and local habits.

    One electronic health record.

    HCA Healthcare has completed another major phase of its multiyear MEDITECH Expanse deployment, bringing 34 additional hospitals onto the platform across its Capital and North Florida divisions.

    With the latest implementation, 72 HCA hospitals in the United States and United Kingdom are now operating on MEDITECH Expanse. The Capital and North Florida divisions are the first two of HCA’s 15 U.S. divisions to fully implement the platform.

    At first glance, this is another large EHR implementation story.

    It is actually something more important.

    HCA is confronting one of the hardest problems in healthcare technology:

    How do you create consistent clinical workflows across a massive healthcare organization without ignoring how people actually work?

    Installing the same EHR everywhere is one part of that challenge.

    Getting thousands of users across dozens of facilities to use it effectively is another.

    HCA’s MEDITECH Rollout Is Operating at Enormous Scale

    HCA Healthcare is not implementing an EHR in a single community hospital.

    The organization handles approximately 47 million patient encounters annually, according to Becker’s reporting on the latest deployment.

    That scale changes everything.

    The Capital Division includes 18 hospitals across Virginia and New Hampshire. The North Florida Division includes 16 hospitals in Florida. Both have now fully transitioned to MEDITECH Expanse.

    HCA began the large-scale Expanse deployment in 2025. Twenty-two hospitals initially went live, followed by additional waves. Another group of hospitals is scheduled for implementation in October 2026 as the rollout continues across facilities in the U.S. and U.K.

    HCA’s objective is not simply replacing software.

    The health system says Expanse is helping create a more connected and standardized foundation for clinical information and workflows across the enterprise.

    That word, standardized, is critical.

    Because one of the biggest promises of enterprise EHR consolidation is that clinicians across different facilities can begin operating from a more consistent digital foundation.

    But that promise does not automatically become reality when the software goes live.

    Standardizing the EHR Is Easier Than Standardizing Human Behavior

    A health system can configure one medication administration workflow.

    It can establish one documentation framework.

    It can standardize order sets.

    It can create enterprise-wide security roles.

    It can develop shared templates.

    It can consolidate patient information.

    But hospitals do not begin an EHR implementation as blank slates.

    Each facility already has its own history.

    Its own processes.

    Its own shortcuts.

    Its own terminology.

    Its own workarounds.

    Its own experienced employees who have performed certain tasks the same way for years.

    That means a systemwide EHR implementation is not simply a technology migration.

    It is organizational change at an enormous scale.

    A nurse who previously documented medication administration one way may now have a different workflow.

    A physician accustomed to finding results in a particular location may need to change years of muscle memory.

    Laboratory staff may experience different navigation.

    Emergency department teams may need to rethink documentation, tracking and orders.

    Registration staff may encounter new processes.

    Revenue cycle teams may see different workflows.

    Even when the new system is technically better, people still have to learn it.

    That is where implementation success becomes dependent on adoption.

    A Successful Go-Live Can Still Produce Frustrated Users

    Healthcare organizations often measure go-live success through technical metrics.

    Did the system launch on time?

    Were interfaces functioning?

    Did patient data migrate correctly?

    Were orders transmitted?

    Did pharmacy systems communicate correctly?

    Did billing continue?

    Did critical applications remain available?

    All of those questions matter.

    But there is another layer that can be harder to measure.

    Can users actually work efficiently?

    A system can be technically operational while clinicians struggle with unfamiliar workflows.

    A physician may successfully place an order but take significantly longer to find the correct workflow.

    A nurse may complete documentation correctly but require repeated assistance.

    A scheduler may eventually complete a task after trying several screens.

    Technically, the system worked.

    Operationally, friction was created.

    At the scale of an organization such as HCA, small amounts of friction can multiply quickly.

    If a workflow adds even one unnecessary minute to a frequently repeated task, the cumulative impact across millions of encounters can become enormous.

    That is why user proficiency should be treated as an implementation metric, not simply a training responsibility.

    MEDITECH Expanse Is Becoming More Important Across HCA

    HCA’s continued rollout also demonstrates that MEDITECH remains a major force in the hospital EHR market.

    While Epic receives a large share of attention because of its dominance among large U.S. health systems, MEDITECH continues to maintain a significant position, particularly across organizations such as HCA.

    Becker’s reported earlier this year that several hospitals had either implemented or selected MEDITECH Expanse, including Schneck Medical Center, Hendry Regional Medical Center, Parrish Healthcare and Western Missouri Medical Center. HCA’s enterprise deployment is considerably larger in scale.

    The broader U.S. EHR landscape therefore continues to require expertise across multiple platforms.

    Epic.

    Oracle Health.

    MEDITECH.

    And other systems serving different portions of the healthcare market.

    For healthcare IT professionals and clinical support teams, platform diversity matters.

    A workflow guidance strategy built only around the dominant vendor will not address the reality of American healthcare.

    MEDITECH Workflows Still Require Real-World Support

    The challenges users experience during an Expanse implementation are often familiar to anyone who has supported an EHR go-live.

    Where do I document this?

    Where is the medication administration record?

    How do I locate the patient’s previous results?

    How do I complete blood administration documentation?

    Where do I update the care plan?

    How do I find the appropriate flowsheet?

    Where do I enter this order?

    What is the correct workflow for discharge?

    How does this task differ between inpatient and emergency department workflows?

    Those questions sound simple outside the clinical environment.

    Inside a hospital, they matter.

    A clinician may be asking one of those questions while simultaneously managing medications, monitoring a deteriorating patient, responding to another department and documenting care.

    The value of EHR support comes from reducing the time between the question and the answer.

    Go-Live Support Should Follow the Workflow, Not the Software Manual

    Traditional EHR education frequently begins with structured training.

    That training is necessary.

    But real work rarely follows a training script.

    A classroom scenario may explain the standard workflow.

    A real patient may present circumstances that require the user to remember three different workflows at once.

    This is why at-the-elbow support has historically played such an important role during large EHR implementations.

    Experienced support staff can observe what the user is trying to accomplish and help translate that task into the appropriate system workflow.

    They can also identify patterns.

    If dozens of nurses repeatedly ask the same question, the problem may not be individual users.

    It may be training.

    It may be configuration.

    It may be workflow design.

    It may be terminology.

    It may be that a process is simply harder than expected.

    That information is valuable because go-live support can function as a real-time feedback system for the implementation team.

    Large Rollouts Make Knowledge Consistency Critical

    Now consider the challenge across 34 hospitals.

    One support specialist may explain a workflow one way.

    Another may explain it differently.

    One facility may develop an unofficial workaround.

    Another may interpret a workflow differently.

    Local tip sheets may begin circulating.

    Screenshots become outdated.

    Email instructions are forwarded months later.

    Information fragments.

    This creates another problem for enterprise EHR deployments:

    How do you make sure everyone receives the same current answer?

    Large health systems need more than support availability.

    They need support consistency.

    Users should be able to access guidance aligned with the organization’s approved workflow rather than whichever explanation happens to be available at that moment.

    That is where centralized EHR knowledge becomes increasingly important.

    The Support Problem Does Not End When the Command Center Closes

    Major implementations often receive extensive resources around launch.

    Command centers operate around the clock.

    Trainers are available.

    Super users receive special preparation.

    At-the-elbow consultants circulate through clinical departments.

    Support tickets receive heightened attention.

    Then the implementation stabilizes.

    Temporary staff leave.

    Command centers close.

    Project teams move to the next facility.

    But the hospital keeps hiring.

    New nurses arrive.

    New physicians join.

    Travel clinicians start assignments.

    Existing employees transfer departments.

    Rarely used workflows are forgotten.

    Updates change the system.

    Optimization introduces new processes.

    The organization may technically be “live,” but learning continues indefinitely.

    For an enterprise rollout occurring in waves, this creates an interesting challenge.

    One hospital may be in active go-live.

    Another may be stabilizing.

    Another may have been using the system for months.

    Another may be preparing for its implementation.

    The organization simultaneously has users at several stages of EHR maturity.

    Traditional one-time training cannot fully address that environment.

    HCA’s Rollout Shows Why EHR Knowledge Must Become Infrastructure

    Healthcare systems increasingly treat interoperability, cybersecurity, analytics and data platforms as permanent infrastructure.

    Workflow knowledge should be viewed similarly.

    The ability to answer questions such as “How do I perform this task in the EHR?” should not depend exclusively on whether a trainer happens to be nearby.

    It should be an organizational capability.

    That means health systems need ways to capture, maintain and deliver approved workflow guidance continuously.

    And increasingly, artificial intelligence can help make that information easier to access.

    Instead of navigating folders containing hundreds of PDFs, users should increasingly be able to ask a workflow question naturally and receive concise guidance relevant to the task.

    That does not mean handing clinical decisions to AI.

    There is an important difference between clinical decision-making and EHR workflow guidance.

    A workflow support tool does not need to determine what treatment a patient should receive.

    It can help a trained healthcare professional understand how to execute an appropriate system workflow.

    That distinction becomes particularly important when designing AI support tools for healthcare environments.

    Where GoLiveX Fits

    The HCA deployment reflects exactly the environment GoLiveX is designed to support.

    GoLiveX provides AI-powered workflow guidance across major EHR platforms including MEDITECH, Epic and Oracle Health/Cerner.

    The objective is straightforward:

    Help healthcare professionals find the workflow information they need when they need it.

    During go-live, that can complement at-the-elbow support.

    During stabilization, it can help answer recurring questions.

    During normal operations, it can reinforce workflows users may not perform frequently.

    During onboarding, it can help new staff navigate unfamiliar systems.

    During optimization, updated guidance can help organizations reinforce changed processes.

    GoLiveX is designed around EHR workflow guidance without requiring protected health information, allowing the platform to focus on the operational question rather than the patient’s clinical record.

    That model becomes increasingly relevant as health systems operate large, standardized EHR environments across multiple facilities.

    The Next Phase of EHR Success Is Consistency

    HCA’s MEDITECH rollout is a reminder that modern EHR projects are no longer simply hospital technology implementations.

    They are enterprise operating model transformations.

    The software may be standardized.

    The patient record may be unified.

    The workflows may be designed centrally.

    But the benefits only materialize when thousands of people can execute those workflows correctly and efficiently.

    That requires more than installation.

    It requires readiness.

    Training.

    At-the-elbow support.

    Consistent workflow guidance.

    Optimization.

    And long-term reinforcement.

    Thirty-four additional HCA hospitals have now made the transition to MEDITECH Expanse.

    More will follow.

    The technical achievement is significant.

    The bigger opportunity is what comes next:

    Turning dozens of individual hospitals using the same software into a healthcare organization that can actually operate from a shared digital foundation.

    That is where the real value of EHR standardization begins.

    About GoLiveX

    GoLiveX is an AI-powered EHR workflow guidance platform designed to help healthcare professionals navigate Epic, Oracle Health/Cerner, MEDITECH and other clinical systems. GoLiveX provides on-demand workflow guidance without requiring protected health information, supporting clinicians, trainers and healthcare IT teams during implementation, go-live, stabilization, optimization and everyday EHR use.


    SEO Publishing Block

    Recommended SEO Title:
    HCA Moves 34 More Hospitals to MEDITECH Expanse: Why EHR Workflow Standardization Matters

    URL Slug:
    hca-meditech-expanse-go-live-ehr-workflow-standardization

    Primary / Focus Keyword:
    MEDITECH Expanse go-live

    Secondary / Related Keywords:
    MEDITECH Expanse, HCA Healthcare MEDITECH, MEDITECH implementation, MEDITECH training, MEDITECH go-live support, EHR workflow standardization, EHR implementation support, MEDITECH workflow support, hospital EHR implementation, EHR training, at-the-elbow support, clinical workflow support, EHR adoption, healthcare IT implementation

    Meta Description:
    HCA Healthcare has moved 34 more hospitals to MEDITECH Expanse. The massive rollout shows why standardized workflows, clinician training and continuous EHR support matter after go-live.

    Recommended Category:
    EHR Implementation & Go-Live

    Suggested Tags:
    MEDITECH, MEDITECH Expanse, HCA Healthcare, EHR Go-Live, EHR Training, Clinical Workflows, At-the-Elbow Support, Healthcare IT, EHR Optimization, GoLiveX

    Suggested Social Headline:
    34 Hospitals Just Went Live on MEDITECH. Installing the Same EHR Is Only Half the Job.

    Source Story:
    Becker’s Hospital Review, “34 more HCA hospitals go live on Meditech,” published September 14, 2026. HCA now has 72 hospitals in the U.S. and U.K. running MEDITECH Expanse as its multiyear enterprise rollout continues.

  • Oracle Health’s New Oncology EHR Shows Why EHR Training Can No Longer End at Go-Live

    Oracle Health’s New Oncology EHR Shows Why EHR Training Can No Longer End at Go-Live

    The electronic health record is changing again.

    For years, hospitals focused on digitizing documentation, orders, scheduling, results, billing and clinical communication.

    Then came interoperability.

    Then mobile access.

    Then ambient documentation.

    Now the next transformation is arriving directly inside the EHR: artificial intelligence that does more than summarize information. It can help clinicians prepare for encounters, retrieve patient context, support documentation, recommend next steps and increasingly participate in clinical workflows.

    Oracle Health’s latest announcement makes that transition impossible to ignore.

    Oracle has unveiled a new oncology EHR built on its AI-powered ambulatory platform, combining specialty workflows with connected patient information, clinical decision support and embedded AI agents designed specifically around cancer care.

    That is important technology news.

    But for hospitals and clinical teams, it creates an equally important operational question:

    How do you prepare thousands of healthcare professionals for an EHR that no longer stays functionally static after implementation?

    That may become one of healthcare IT’s biggest challenges over the next several years.

    Oracle Is Building AI Directly Into the Oncology Workflow

    According to Becker’s Hospital Review, Oracle Health introduced its oncology-focused EHR at the Oracle Health and Life Sciences Summit in Orlando.

    The platform is designed to support oncology care from diagnosis through treatment and follow-up, across inpatient and outpatient settings. Oracle says it combines oncology workflows, information from multiple data sources, connected patient records and AI-driven clinical intelligence.

    An AI-powered assistant for oncologists is expected to create patient snapshots and pre-visit summaries, help clinicians prepare for tumor boards, support guideline-grounded treatment planning and carry clinical decisions into downstream activities including orders, referrals, documentation and coding.

    Think about what that means from a workflow perspective.

    A traditional EHR implementation might teach a provider:

    Where do I find the patient’s information?

    Where do I document?

    How do I enter the order?

    How do I send the referral?

    How do I complete the encounter?

    An AI-enabled EHR introduces another layer:

    What did the AI summarize?

    Where did that information come from?

    What should I review before acting on it?

    How do I modify the recommendation?

    What happens after I accept it?

    Which parts of the workflow are automated?

    Where does clinician responsibility begin and end?

    That changes the nature of EHR proficiency.

    Healthcare Is Moving From EHR Navigation to EHR Collaboration

    The first generations of EHR training were largely navigation-based.

    Users learned where things were located and how to complete required tasks.

    That is still necessary.

    But the emerging EHR environment requires something more sophisticated.

    Clinicians will increasingly interact with software that can interpret information, summarize records, suggest actions and initiate parts of workflows.

    Oracle’s oncology platform is part of a broader trend.

    Becker’s recently described the EHR as becoming healthcare AI’s “front door” as major vendors embed AI tools directly into the systems clinicians already use.

    Oracle has also launched a clinical AI agent for nurses that operates inside its EHR. The nursing tool includes voice-enabled charting, patient information search and acute nursing summaries intended to help nurses understand a patient’s history and condition and complete documentation closer to real time.

    Oracle previously introduced an AI agent for physicians and has expanded the technology into areas such as AI-assisted chart review, clinician-controlled dictation and coding support.

    This is not an isolated product feature.

    It represents a fundamental shift in how clinicians will interact with healthcare technology.

    The EHR is becoming less like a digital filing system and more like an active participant in the workflow.

    That Creates a New Training Problem

    Imagine a hospital preparing for a conventional EHR go-live.

    Employees complete training before launch.

    Super users are identified.

    At-the-elbow support teams arrive.

    A command center opens.

    The system goes live.

    After several weeks or months, the organization gradually transitions from implementation mode into normal operations.

    That model assumes that the workflows users learned before go-live will remain relatively stable.

    AI challenges that assumption.

    An AI-enabled EHR can gain new capabilities without requiring the organization to replace the underlying platform.

    A documentation tool may be introduced.

    Then automated summaries.

    Then nursing agents.

    Then coding assistance.

    Then specialty-specific workflows.

    Then new decision-support capabilities.

    Each addition changes how someone performs a job they may already believe they know how to perform.

    That means EHR education increasingly becomes continuous.

    Oncology Makes the Challenge Even More Important

    Cancer care demonstrates why this matters.

    Oncology workflows are not simple, linear transactions.

    A patient’s care may involve oncologists, surgeons, radiologists, pathologists, pharmacists, nurses, genetic counselors and other specialists.

    Treatment decisions can depend on pathology, imaging, laboratory results, molecular testing, medications, previous therapies, comorbidities and evolving clinical guidelines.

    Information accumulates longitudinally.

    The patient’s story becomes more complicated over time.

    An AI assistant capable of organizing that information could reduce cognitive and administrative burden.

    But introducing AI into such an environment also means clinicians must understand the technology well enough to use it appropriately.

    The challenge is no longer simply:

    “How do I use Oracle Health?”

    It becomes:

    “How do I use this specific Oracle Health oncology workflow, with these AI capabilities, in this clinical scenario?”

    That difference matters enormously for healthcare training and support.

    Static Training Materials Will Struggle to Keep Up

    Healthcare organizations have traditionally relied heavily on training manuals, tip sheets, classroom sessions, videos and internal knowledge bases.

    Those resources remain useful.

    But static documentation has an obvious weakness in a rapidly changing EHR environment.

    It becomes outdated.

    If a workflow changes but the tip sheet does not, users may receive inaccurate guidance.

    If a new AI feature appears, employees may not understand it.

    If functionality differs between specialties, generic training materials may provide an incomplete answer.

    If someone joins the organization months after implementation, they may inherit a collection of documentation created during several different phases of the deployment.

    This is one reason healthcare organizations should begin treating EHR workflow knowledge as living infrastructure rather than a collection of training documents.

    Users need access to current guidance at the moment the question occurs.

    The Question Is No Longer Just “Can the EHR Do This?”

    As AI capabilities spread across EHR platforms, health systems should begin asking a different set of questions.

    Do clinicians know the feature exists?

    Healthcare organizations frequently invest in technology that employees underuse simply because users do not know what is available.

    Do clinicians understand how it changes their workflow?

    Adding AI to a process does not automatically make the process intuitive.

    Can users get help while they are working?

    A clinician encountering a new function during a busy clinic session cannot always leave the workflow to search through training materials.

    Can the organization keep guidance synchronized with system changes?

    Continuous software evolution requires continuous knowledge maintenance.

    Can support teams identify where users are repeatedly struggling?

    Recurring questions can reveal where additional training, configuration or optimization is needed.

    These questions should become part of the AI deployment conversation.

    AI Does Not Eliminate the Need for EHR Support

    There is an understandable temptation to assume that smarter software eventually eliminates the need for training.

    It may actually do the opposite.

    AI can make software easier to use while simultaneously making the underlying workflow more sophisticated.

    Consider a clinical AI assistant that produces a summary.

    The clinician no longer needs to manually search through dozens of notes.

    That is easier.

    But now the clinician needs to understand how to verify the summary, how the system uses the information, where the original source data can be reviewed and what happens when the AI-generated output is incorporated into clinical documentation or downstream actions.

    Convenience and complexity can exist at the same time.

    That is why human readiness will remain critical.

    This Is Where the Go-Live Model Must Evolve

    The traditional idea of a “go-live” suggests a major beginning followed by gradual stabilization.

    That concept still applies to large implementations.

    But AI is creating smaller go-lives continuously.

    A new agent may effectively represent a new workflow launch.

    A major upgrade can alter how clinicians document.

    A new specialty module can change an entire department’s processes.

    An organization activating ambient documentation may need to retrain users even though the underlying EHR has been running for years.

    A new AI search capability can change how clinicians retrieve information.

    The future may therefore require healthcare organizations to operate with a state of continuous go-live readiness.

    Training, support and optimization become ongoing capabilities rather than temporary implementation activities.

    GoLiveX and the Continuous EHR Learning Model

    This evolution closely matches the problem GoLiveX is designed to address.

    GoLiveX provides AI-powered workflow guidance for healthcare professionals working across major EHR environments including Epic, Oracle Health/Cerner and MEDITECH.

    The objective is not to replace formal training, implementation teams, analysts or at-the-elbow specialists.

    It is to extend their knowledge.

    Instead of requiring a user to remember every workflow learned during training, the user can seek guidance when the workflow is actually needed.

    Instead of treating support as something available only during implementation, healthcare organizations can make workflow assistance available throughout the lifecycle of the EHR.

    And because GoLiveX is designed for workflow guidance without requiring protected health information, the focus remains on helping users understand the system rather than analyzing an individual patient’s record.

    That distinction becomes increasingly important as AI expands throughout healthcare.

    The EHR Is Becoming an Intelligent Workspace

    Oracle’s oncology announcement is significant because it provides another glimpse of what the EHR is becoming.

    Not simply a repository.

    Not simply a documentation tool.

    Not simply a billing engine.

    An intelligent clinical workspace.

    The same transformation is happening across healthcare technology.

    Epic is expanding AI throughout its ecosystem.

    Oracle is developing clinical AI agents for physicians, nurses and specialty workflows.

    Health systems are building their own agents around EHR data and operational processes.

    Twenty-five health systems recently participated in an Epic initiative to build AI agents for clinical and operational workflows, another indication of how rapidly this environment is developing.

    The direction is becoming clear.

    The harder question is whether healthcare organizations can prepare their people as quickly as vendors can develop the technology.

    The Next EHR Challenge Is Adoption at the Speed of AI

    Hospitals have already learned an expensive lesson from decades of healthcare IT implementations:

    Installing technology does not guarantee adoption.

    And adoption does not guarantee proficiency.

    AI does not change that equation.

    It raises the stakes.

    As systems such as Oracle Health introduce increasingly intelligent clinical workflows, successful deployment will depend on more than whether the software functions correctly.

    Healthcare organizations will need clinicians who understand what changed, how the new workflow works and where to get immediate help when they do not know the answer.

    That means the future of EHR implementation cannot end with training before go-live.

    It must include continuous learning after go-live.

    Oracle’s new oncology EHR may be designed specifically for cancer care, but the message extends far beyond oncology.

    The EHR is becoming intelligent.

    Now healthcare’s training and support infrastructure has to become intelligent too.

    About GoLiveX

    GoLiveX is an AI-powered EHR workflow guidance platform designed to help healthcare professionals navigate Epic, Oracle Health/Cerner, MEDITECH and other clinical systems. GoLiveX provides on-demand workflow guidance without requiring protected health information, helping clinicians, trainers and healthcare support teams access EHR knowledge during implementation, go-live, stabilization, optimization and everyday clinical use.


    SEO Publishing Block

    Recommended SEO Title:
    Oracle Health’s AI Oncology EHR Shows Why Continuous EHR Training Is the Next Challenge

    URL Slug:
    oracle-health-ai-oncology-ehr-continuous-training

    Primary / Focus Keyword:
    AI EHR training

    Secondary / Related Keywords:
    Oracle Health EHR, Oracle Health AI, Oracle Clinical AI Agent, Cerner AI, EHR workflow training, AI clinical workflows, EHR adoption, EHR workflow support, healthcare AI training, continuous EHR training, clinician EHR support, oncology EHR, EHR optimization, AI-powered EHR

    Meta Description:
    Oracle Health’s new AI-powered oncology EHR shows how embedded clinical AI is changing EHR workflows and why hospitals need continuous training and workflow support beyond go-live.

    Recommended Category:
    AI & EHR Innovation

    Suggested Tags:
    Oracle Health, Cerner, Clinical AI, EHR Training, Oncology, Healthcare AI, EHR Workflows, EHR Optimization, Clinical Informatics, GoLiveX

    Suggested Social Headline:
    The EHR Is Learning New Skills Faster Than Clinicians Can Be Trained. That Is Healthcare’s Next IT Problem.

    Source Story:
    Becker’s Hospital Review, “Oracle Health unveils oncology EHR with AI-driven cancer care tools,” published September 24, 2026.

  • Penn State Health’s Systemwide Epic Go-Live Is a Reminder: EHR Success Starts Before Day One

    Penn State Health’s Systemwide Epic Go-Live Is a Reminder: EHR Success Starts Before Day One

    On October 31, Penn State Health plans to make one of the most consequential technology changes a health system can undertake.

    Epic will go live across the organization.

    For patients, the most visible change may be simpler access to care. For clinicians, nurses, schedulers, revenue cycle teams, IT staff and operational leaders, however, the transition represents something much larger: thousands of workflows, habits, screens, decisions and daily processes changing at the same time.

    And that is where an EHR implementation either becomes transformational or painfully disruptive.

    Penn State Health says the systemwide launch will create a unified electronic health record and billing environment and introduce Epic MyChart as its patient portal. MyChart will replace five separate patient portals, giving patients a single place to communicate with care teams, access test results, schedule appointments, manage prescriptions, join virtual visits and review their health information.

    The technology story is significant.

    But the human story may matter even more.

    A Go-Live Is Not the Finish Line

    Health systems often spend years preparing for a major EHR implementation.

    Infrastructure is built. Interfaces are tested. Data is migrated. Workflows are mapped. Security roles are configured. Training environments are established. Thousands of employees complete required education.

    Then comes go-live.

    That moment can create the impression that the implementation is complete.

    It isn’t.

    In many ways, the most important phase has just begun.

    The real test starts when a physician needs to enter an unfamiliar order while patients are waiting.

    When an emergency department nurse cannot immediately locate the documentation workflow previously completed almost automatically.

    When a scheduler encounters a scenario that wasn’t covered during training.

    When a pharmacist sees information displayed differently.

    When a clinician understands the clinical task perfectly but does not yet know how the new system expects that task to be completed.

    These are not necessarily software failures.

    They are the normal consequences of changing the digital operating system of a healthcare organization.

    That distinction matters.

    Penn State Health says the unified Epic environment is intended to streamline workflows, reduce manual tasks, improve communication and give clinicians and support staff greater visibility across hospitals and outpatient practices. The organization also expects the platform to support research, education, data use and emerging AI capabilities.

    But those benefits depend on people being able to use the platform effectively.

    2026 Is Becoming a Major Year for EHR Change

    Penn State Health is not making this transition in isolation.

    Hospitals across the country are implementing, replacing or consolidating electronic health record systems in 2026.

    Becker’s reported this month that EHR migrations have become some of healthcare’s largest capital technology projects, ranging from smaller hospital implementations to projects valued in the hundreds of millions or even more than $1 billion. Health systems including Adventist Health, Northwell Health, Sarasota Memorial Health Care System and multiple Department of Veterans Affairs facilities have been part of major EHR transitions this year.

    Epic continues to expand its presence as well. According to KLAS data cited by Becker’s, Epic accounted for 43.7% of the U.S. acute care hospital EHR market by hospital share at the end of 2025, compared with 42.3% a year earlier.

    The scale of these migrations creates an important reality for healthcare organizations:

    EHR readiness is becoming an operational competency, not a one-time IT project.

    Health systems need more than technically successful implementations.

    They need clinicians who can work safely and confidently inside those systems from the moment they go live.

    Training Alone Cannot Prepare Users for Every Workflow

    Formal EHR training is essential.

    It establishes the fundamentals users need before entering a production environment.

    But there is a limitation that nearly every large implementation eventually encounters: classroom learning and real clinical work are not the same thing.

    A physician may understand how to place an order during training but encounter a different combination of clinical circumstances during an actual shift.

    A nurse may know where documentation belongs but struggle to remember the exact navigation path while managing multiple patients.

    A new employee may join months after the implementation team has left.

    A workflow may change after optimization.

    An Epic upgrade may introduce new functionality.

    A department may use the same EHR differently because of specialty-specific workflows.

    That gap between knowing the clinical task and knowing how to execute it efficiently inside the EHR is where support becomes critical.

    Traditional training prepares users.

    Go-live support helps users perform.

    Optimization helps them improve.

    Healthcare organizations need all three.

    Why At-the-Elbow Support Still Matters

    One of the most effective resources during a major EHR transition remains remarkably simple: placing knowledgeable support where clinicians are actually working.

    At-the-elbow support allows users to receive immediate assistance without abandoning the clinical workflow to search through lengthy documentation, submit a help desk ticket or wait for someone to return a call.

    The value becomes especially obvious during the first days of a go-live.

    A 30-second answer can prevent several minutes of confusion.

    A workflow clarification can keep a patient moving.

    A quick explanation can prevent the same mistake from being repeated throughout a shift.

    And one experienced support specialist can identify patterns affecting an entire department.

    Intermountain Health demonstrated the scale at which this support can be deployed during its major Epic launch in September 2025. The health system told Becker’s it used around-the-clock command centers, at-the-elbow assistance, super-user coverage and an Epic coaching hotline during the initial transition period. The organization also emphasized workflow testing and caregiver training before go-live.

    That combination is important.

    Technology readiness and human readiness cannot be separated.

    The Support Model Is Also Changing

    There is another challenge.

    Hospitals cannot maintain massive physical go-live teams forever.

    Traditional at-the-elbow support is extremely valuable during implementation, but eventually outside consultants leave, temporary command centers close and organizations transition into normal operations.

    The questions do not disappear.

    New employees arrive.

    Experienced users forget infrequently used workflows.

    Departments change processes.

    EHR vendors release upgrades.

    Hospitals enable new modules.

    AI functionality enters existing workflows.

    Optimization creates new ways of completing familiar tasks.

    Healthcare organizations therefore need to think beyond the traditional model of intensive support for several weeks followed by a dramatic reduction in assistance.

    The next generation of EHR support will increasingly combine human expertise with intelligent, always-available workflow guidance.

    A clinician encountering an unfamiliar workflow should not necessarily have to search through a 60-page training guide or wait for a help desk response.

    They should be able to ask a clear question and receive concise, workflow-specific guidance when they need it.

    That does not eliminate trainers, analysts, super users or support teams.

    It makes their expertise easier to access and allows human teams to concentrate on more complicated issues.

    AI Is Making This Even More Important

    The EHR itself is changing.

    Epic is increasingly adding artificial intelligence across clinical workflows, while Oracle Health and other vendors are doing the same.

    Becker’s recently described the EHR as an emerging “front door” for healthcare AI as vendors and health systems integrate AI functionality more deeply into existing clinical environments.

    Epic is already introducing AI tools for areas including clinical documentation and information synthesis. Hospitals have begun deploying and testing these capabilities in real workflows.

    Penn State Health has also identified data and AI capabilities as part of the strategic value expected from its new Epic platform.

    This creates another layer of readiness.

    Health systems will not only need to teach clinicians how to use an EHR.

    They will increasingly need to help clinicians understand how AI interacts with the EHR, where automated recommendations appear, what new workflows are available, what still requires human review and how those tools should fit into clinical practice.

    The learning curve is not getting smaller.

    It is becoming continuous.

    Five Questions Health Systems Should Ask Before Go-Live

    Before a major EHR launch, healthcare leaders should be able to answer several practical questions:

    Can clinicians get help in seconds, not minutes?

    When clinical operations are moving quickly, support must be available at the speed of the workflow.

    Are support resources available where the work happens?

    Emergency departments, inpatient units, ambulatory clinics, operating rooms, laboratories and specialty departments have different workflows and different pressures.

    What happens after the go-live consultants leave?

    The support strategy should extend beyond launch week.

    Can the organization identify recurring workflow problems?

    Repeated questions are valuable data. They can reveal training deficiencies, confusing configuration, usability problems or workflows that need optimization.

    How will new employees learn the system six months later?

    A mature EHR adoption strategy must support onboarding and ongoing learning, not only the original implementation.

    These questions are increasingly important as healthcare organizations invest hundreds of millions of dollars in digital transformation.

    Penn State Health’s Real Opportunity Begins October 31

    Penn State Health’s Epic implementation has the potential to accomplish something substantial.

    A single EHR can create a more connected clinical environment.

    A unified patient portal can simplify digital access.

    Standardized workflows can reduce fragmentation.

    Shared information can strengthen care coordination.

    Integrated data can support research, analytics and AI.

    But none of those outcomes occur simply because an EHR has been installed.

    Technology creates capability.

    People create results.

    That is why the most successful EHR implementations should ultimately be measured not simply by whether the system went live on schedule, but by what happens afterward.

    Can clinicians find what they need?

    Can nurses document efficiently?

    Can providers place orders confidently?

    Can support teams resolve problems quickly?

    Can new users become proficient faster?

    Can the organization continuously improve the workflows it spent years building?

    On October 31, Penn State Health will turn on Epic across the health system.

    The software launch will happen in a day.

    The work of adoption, optimization and continuous learning will continue long after it.

    And that may ultimately determine the real return on the investment.

    About GoLiveX

    GoLiveX is an AI-powered EHR workflow guidance platform designed to help healthcare professionals navigate Epic, Oracle Health/Cerner, MEDITECH and other clinical systems. It provides on-demand workflow guidance without requiring protected health information, helping clinicians and healthcare support teams find answers when they need them during go-live, stabilization, optimization and ongoing EHR use.


    SEO Publishing Block

    Recommended SEO Title:
    Penn State Health Epic Go-Live Highlights the Need for EHR Readiness and Clinical Workflow Support

    URL Slug:
    penn-state-health-epic-go-live-ehr-readiness-support

    Primary / Focus Keyword:
    Epic go-live support

    Secondary Keywords:
    Epic implementation, EHR go-live, EHR implementation support, Epic training, at-the-elbow support, EHR workflow support, clinical workflow training, Epic go-live readiness, healthcare IT implementation, clinician EHR training, Penn State Health Epic, EHR optimization, AI EHR support

    Meta Description:
    Penn State Health will launch Epic systemwide on October 31. Here is why clinician readiness, at-the-elbow support and continuous EHR workflow guidance are critical to successful go-live adoption.

    Recommended Category:
    EHR Implementation & Go-Live

    Suggested Tags:
    Epic, Penn State Health, EHR Go-Live, Healthcare IT, EHR Training, At-the-Elbow Support, Clinical Workflows, EHR Optimization, Digital Health

    Suggested Social Headline:
    Penn State Health Is Going Live With Epic. The Hard Part Starts After the Switch Is Flipped.

    Source Story:
    Becker’s Hospital Review, “Penn State Health to launch Epic systemwide,” supplemented by Penn State Health’s official Epic implementation announcement.

  • Ambient Clinical Voice Technology: Redefining Intelligent EHR Documentation

    Ambient Clinical Voice Technology: Redefining Intelligent EHR Documentation

    For decades, the promise of Electronic Health Records (EHRs) has been overshadowed by the immense administrative burden placed on providers. Clinicians routinely spend hours beyond their scheduled shifts completing medical charts, leading to widespread burnout. Traditional dictation software helped, but it still required physicians to manually organize their thoughts and navigate complex EHR interfaces.

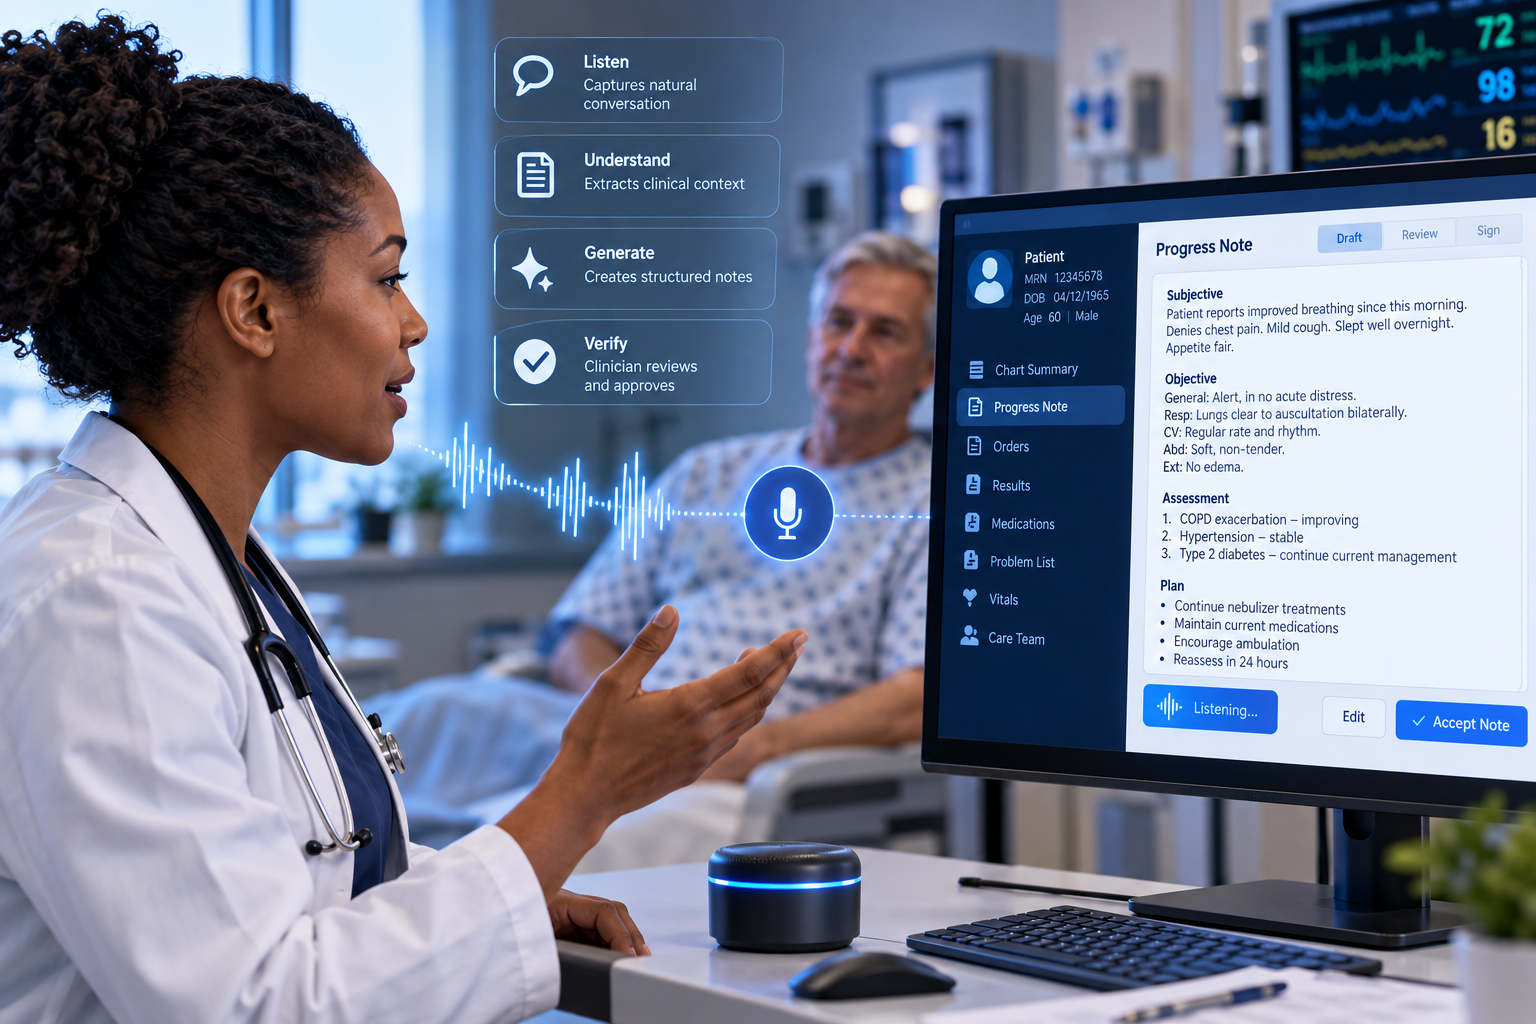
    By 2026, healthcare systems are moving beyond basic dictation toward Ambient Clinical Voice Technology combined with Intelligent Clinical Documentation. These ambient listening systems operate passively in the background of a patient encounter, securely capturing the natural, multi-speaker conversation between the physician and the patient.

    Using advanced AI, these platforms instantly synthesize the dialogue into structured, billing-compliant clinical notes, allowing providers to return their focus entirely to the patient rather than a computer screen.

    Documentation Evolution: Manual Charting vs. Ambient Voice Technology

    Ambient systems shift the EHR from a data-entry repository into an active, context-aware clinical assistant.

    Workflow VectorTraditional EHR DocumentationAmbient Clinical Voice Documentation
    Data CaptureActive; requires manual typing, clicking, or structured dictation commands.Passive; natural language processing listens to the organic patient-provider conversation.
    Note StructuringManual; providers must organize details into subjective, objective, assessment, and plan formats.Automated; AI extracts key clinical details and generates structured templates without changing clinical intent.
    Workflow InterruptionHigh; clinicians look at screens, reducing direct eye contact and patient engagement.Zero; allows for completely hands-free interactions, improving patient trust and engagement.
    Time SavingsMinimal; documentation frequently spills over into “pajama time” after hours.Massive; early studies show up to a 70% reduction in after-hours documentation time.

    The Ambient Documentation Pipeline

    Ambient listening transforms raw exam room dialogue into actionable, interoperable health data.

                     [Patient & Provider Consultation]

                                     │

                     (Natural Conversation & Examination)

                                     │

                                     ▼

                     [Ambient Voice Processing Engine]

                                     │

            (Speaker Diarization & Semantic Intent Extraction)

                                     │

                                     ▼

                  [Intelligent Clinical Documentation Builder]

                                     │

                                     ▼

               [Drafted SOAP Note & Coded Billing Recommendations]

                                     │

                                     ▼

                 [Provider Review, One-Click Sign-Off & EHR Sync]

    Core Features of Ambient EHR Integration

    1. Context-Aware Extraction: The AI automatically filters out casual small talk, pulling only the relevant medical history, reported symptoms, and prescribed treatment plans into the clinical record.
    2. Workflow-Aligned Design: Drafted notes are embedded directly into the provider’s existing clinical workflow, reducing screen clicks and eliminating the need to duplicate patient history.
    3. Immediate Data Availability: By finalizing documentation at the point of care, structured data is immediately available for FHIR-based interoperability, supporting real-time decision-making across the care continuum.

    Key Takeaways

    • Eliminating “Pajama Time”: Automating charting workflows reclaims hours of personal time for providers, directly combatting clinician burnout.
    • Enhanced Patient Interaction: Hands-free documentation restores direct eye contact and conversational flow between doctors and patients.
    • Higher Accuracy: AI-assisted systems capture subtle clinical details that might be forgotten if a note is transcribed hours after the actual appointment.
    • Streamlined Billing: Integrating clinical details natively with correct billing codes accelerates the hospital revenue cycle.
  • Real-Time Hemodynamic Decompensation Prediction: Early Warning Intelligence in Intensive Care Units

    Real-Time Hemodynamic Decompensation Prediction: Early Warning Intelligence in Intensive Care Units

    In critical care and intensive care units (ICUs), hemodynamic instability—driven by septic shock, acute myocardial injury, or hypovolemia—remains a leading cause of patient mortality. When a critically ill patient experiences rapid circulatory collapse, every minute spent before initiating vasopressor support or fluid resuscitation increases the risk of multi-organ failure.

    Historically, ICU teams monitor patients using standard threshold alarms set on bedside vital sign monitors. However, these traditional monitors operate on reactive, single-parameter logic (e.g., sounding an alarm only after mean arterial pressure drops below 65 mmHg). In complex physiological states, compensatory mechanisms (such as peripheral vasoconstriction and elevated heart rate) mask underlying tissue hypoperfusion long before systemic blood pressure drops.

    To prevent sudden cardiovascular collapse, health networks are deploying Real-Time Hemodynamic Decompensation Prediction Engines integrated with Central ICU Telemetry. By processing high-frequency continuous waveforms—including arterial line pressure, central venous pressure, pulse oximetry, and electrocardiography—these engines detect subtle, non-linear physiological decay hours before clinical decompensation occurs.

    Accelerating Critical Care Response: Threshold Alarms vs. Real-Time Predictive Telemetry

    Predictive analytics evaluate multi-parameter trend velocity to alert clinical teams prior to circulatory failure.

    [Continuous High-Frequency Waveform Telemetry Streaming]

                               │

                               ▼

      [GoLiveX Real-Time Hemodynamic Prediction Engine]

                               │

      (Analyzes Pulse Contour, Variability & Compensatory Drift)

                               │

                               ▼

     [Early Decompensation Risk Alert Delivered to ICU Workstation]

    Operational Comparison: Traditional ICU Alarms vs. Real-Time Predictive Analytics

    Clinical VectorLegacy Bedside Threshold AlarmsGoLiveX Real-Time Hemodynamic Engine
    Monitoring LogicSingle-parameter; triggers only when a value crosses a static threshold.Multi-parameter; cross-evaluates complex interactions across vital waveforms.
    Detection WindowReactive; alerts after hypoperfusion and hypotension have already occurred.Predictive; identifies cardiovascular instability 1 to 4 hours before collapse.
    Alarm FatigueHigh; frequent false alarms caused by motion artifacts or momentary spikes.Low; advanced signal processing filters out noise to ensure high alert specificity.
    Intervention StrategyEmergency resuscitation following acute drop in blood pressure.Proactive stabilization, optimization of fluid management, and timely vasopressor initiation.

    Primary Strategic Benefits for Critical Care Units

    1. Early Septic Shock Identification: By analyzing arterial line pulse contour variability alongside heart rate turbulence, algorithms spot subclinical circulatory distress early.
    2. Reduction in Alarm Fatigue: Filtering out transient artifacts cuts unnecessary noise, ensuring ICU staff respond quickly to genuine early-warning alerts.
    3. Closed-Loop Fluid Responsiveness Support: Provides bedside clinicians with precise indices (such as Stroke Volume Variation) to determine whether a patient will benefit from fluid administration or vasopressors.

    Key Takeaways

    • Beyond Reactive Thresholds: Standard alarms fail to catch compensatory physiological mechanisms, delaying life-saving critical care interventions.
    • Continuous Waveform Analytics: High-frequency processing of invasive arterial lines and telemetry surfaces hidden trends hours before hypotension presents.
    • Mitigating Alarm Fatigue: Multi-parameter validation reduces false positives, helping ICU nurses focus on actionable clinical alerts.
    • Proactive Hemodynamic Stabilization: Early detection enables timely fluid and vasopressor management, preventing organ failure and improving ICU survival rates.
  • Real-Time Stroke Triage & Ischemic Penumbra Analytics: Accelerating Thrombolysis in Emergency Care

    Real-Time Stroke Triage & Ischemic Penumbra Analytics: Accelerating Thrombolysis in Emergency Care

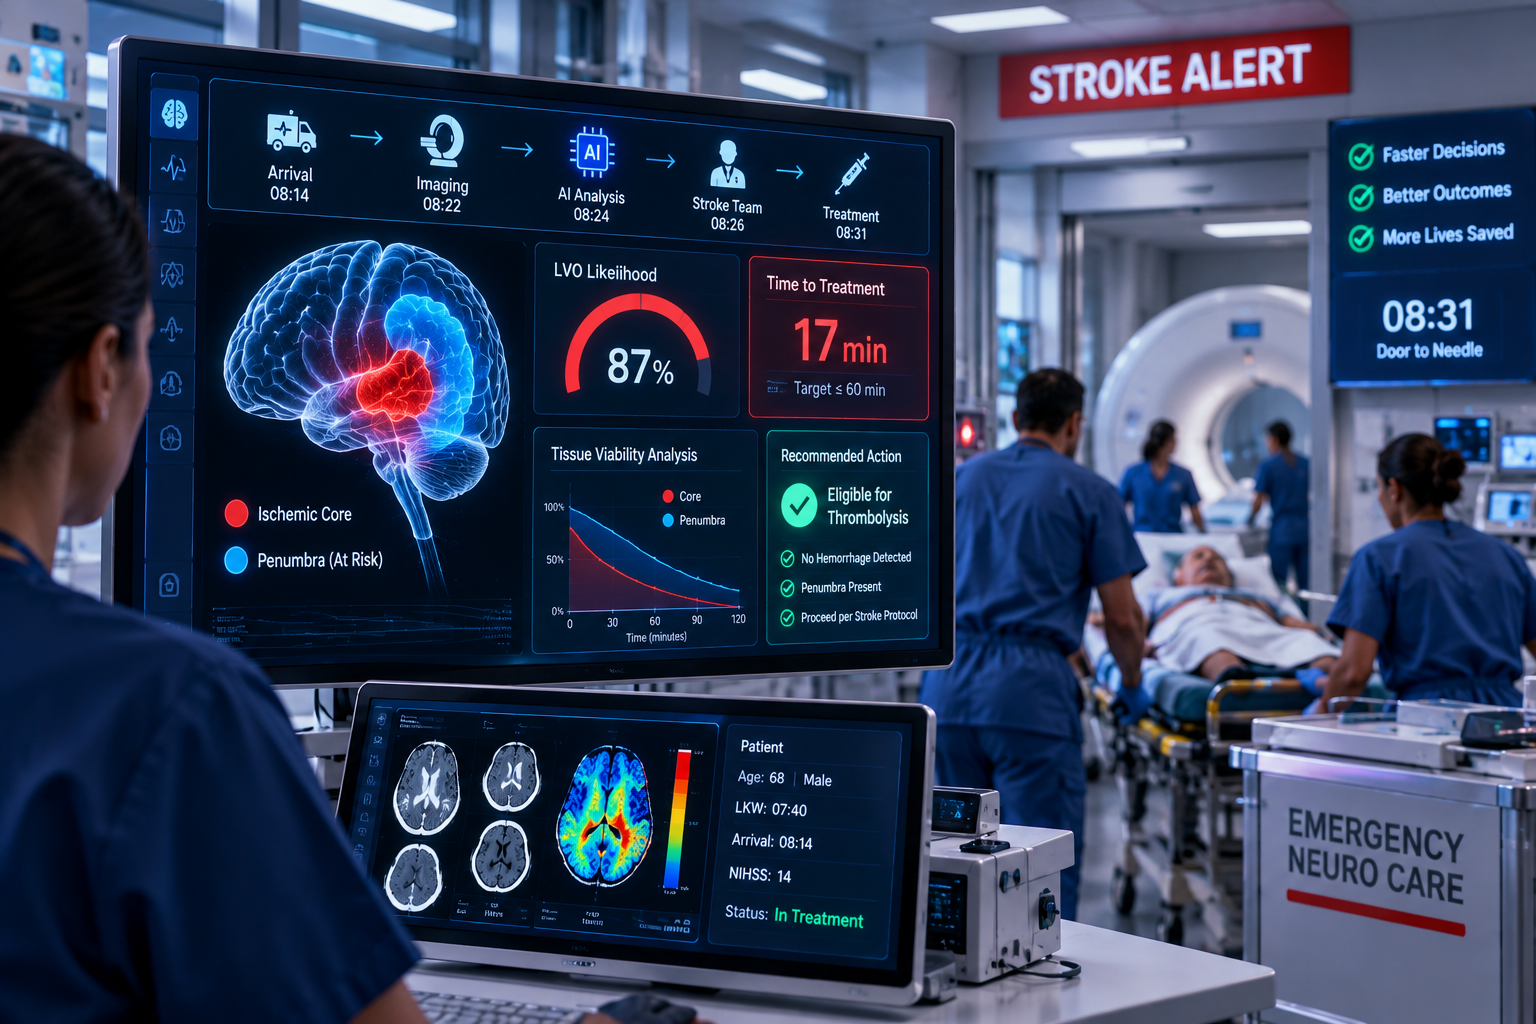
    In emergency stroke management, “time is brain.” When an acute ischemic stroke occurs, millions of neurons die each minute perfusion remains blocked. Minimizing the door-to-needle (DTN) time for intravenous thrombolysis and endovascular thrombectomy (EVT) is the single most critical factor in preventing permanent neurological disability.

    Historically, determining patient candidacy for reperfusion therapy relies on manual review of unenhanced CT scans, CT angiography (CTA), and CT perfusion images by on-call radiologists and neurointerventionalists. In busy emergency departments, waiting for imaging transfers, manual software rendering, and specialist consultation introduces 30 to 60 minutes of critical delay—frequently missing the narrow therapeutic window for salvaging ischemic tissue.

    To accelerate life-saving interventions, health networks are implementing Real-Time Stroke Triage & Penumbra Analytics Engines directly within Emergency Radiology Workflows. By processing raw CT perfusion scans automatically at the scanner console, these engines calculate core-to-penumbra ratios and alert neurovascular stroke teams within minutes of image acquisition.

    Accelerating Neurovascular Care: Manual Review vs. Real-Time Perfusion Analytics

    Automated penumbra analytics eliminate imaging bottlenecks to enable rapid reperfusion decisions.

    [Patient Completes Emergency Brain CT / CTA / CTP Scan]

                                │

                                ▼

         [GoLiveX Real-Time Stroke Perfusion Analytics]

                                │

         (Calculates Ischemic Core vs. Salvageable Penumbra)

                                │

                                ▼

     [Instant EHR / Mobile Alert to Neurointerventional Team]

    Operational Comparison: Traditional Emergency Triage vs. Real-Time Perfusion Analytics

    Clinical VectorLegacy Manual Stroke WorkflowGoLiveX Real-Time Stroke Analytics Engine
    Image ProcessingManual rendering and threshold calculation by radiology staff.Automated instantaneous processing directly at the imaging console.
    Penumbra QuantificationSubjective visual estimation based on multi-slice CT scans.Automated precise volumetric calculation of core infarct vs. penumbra tissue.
    Notification VelocitySequential phone calls following radiology report signature.Simultaneous real-time alerts pushed to stroke team mobile devices.
    Treatment Decision45 to 90 minutes door-to-needle / door-to-puncture time.Under 20 minutes door-to-decision time, accelerating reperfusion therapy.

    Primary Strategic Benefits for Emergency Neurovascular Services

    1. Rapid Penumbra Identification: Advanced volumetric algorithms measure cerebral blood volume (CBV) and cerebral blood flow (CBF) deficits, immediately flagging salvageable brain tissue.
    2. Automated Large Vessel Occlusion (LVO) Detection: High-resolution CTA analysis identifies arterial blockages in the middle cerebral or internal carotid arteries, instantly initiating EVT protocol workflows.
    3. Multi-Disciplinary Mobile Alerts: Radiologists, neurologists, and catheterization lab teams receive synchronized, interactive imaging overlays simultaneously on mobile devices, enabling fast collaborative decision-making.

    Key Takeaways

    • Minimizing Treatment Delays: Automating neuroimaging analysis shortens the time to thrombolysis and endovascular intervention.
    • Precise Penumbra Mapping: Quantitative tissue volume calculations identify patients who will benefit from reperfusion therapy.
    • Instant Team Activation: Automated LVO detection alerts interventional stroke teams simultaneously, cutting door-to-puncture times.
    • Improved Neurological Recovery: Accelerating clinical decision-making preserves brain function and reduces long-term disability for acute stroke patients.
  • Real-Time Perioperative Blood Management: Predictive Transfusion Analytics in High-Risk Surgery

    Real-Time Perioperative Blood Management: Predictive Transfusion Analytics in High-Risk Surgery

    In major cardiovascular, orthopedic, and trauma surgeries, managing acute intraoperative blood loss represents a time-critical clinical challenge. Delayed recognition of rapid hemorrhage leads to severe hypovolemic shock, organ ischemia, and increased perioperative mortality.

    Historically, intraoperative transfusion decisions rely on periodic manual blood draws sent to central laboratories for hemoglobin and hematocrit analysis. However, lab turnaround times often take 20 to 40 minutes—a dangerous delay when a patient is actively hemorrhaging. As a result, surgical teams are often forced to choose between waiting for delayed lab results or empirically ordering massive transfusion protocols, which risks wasting scarce donor blood products and causing transfusion-related complications.

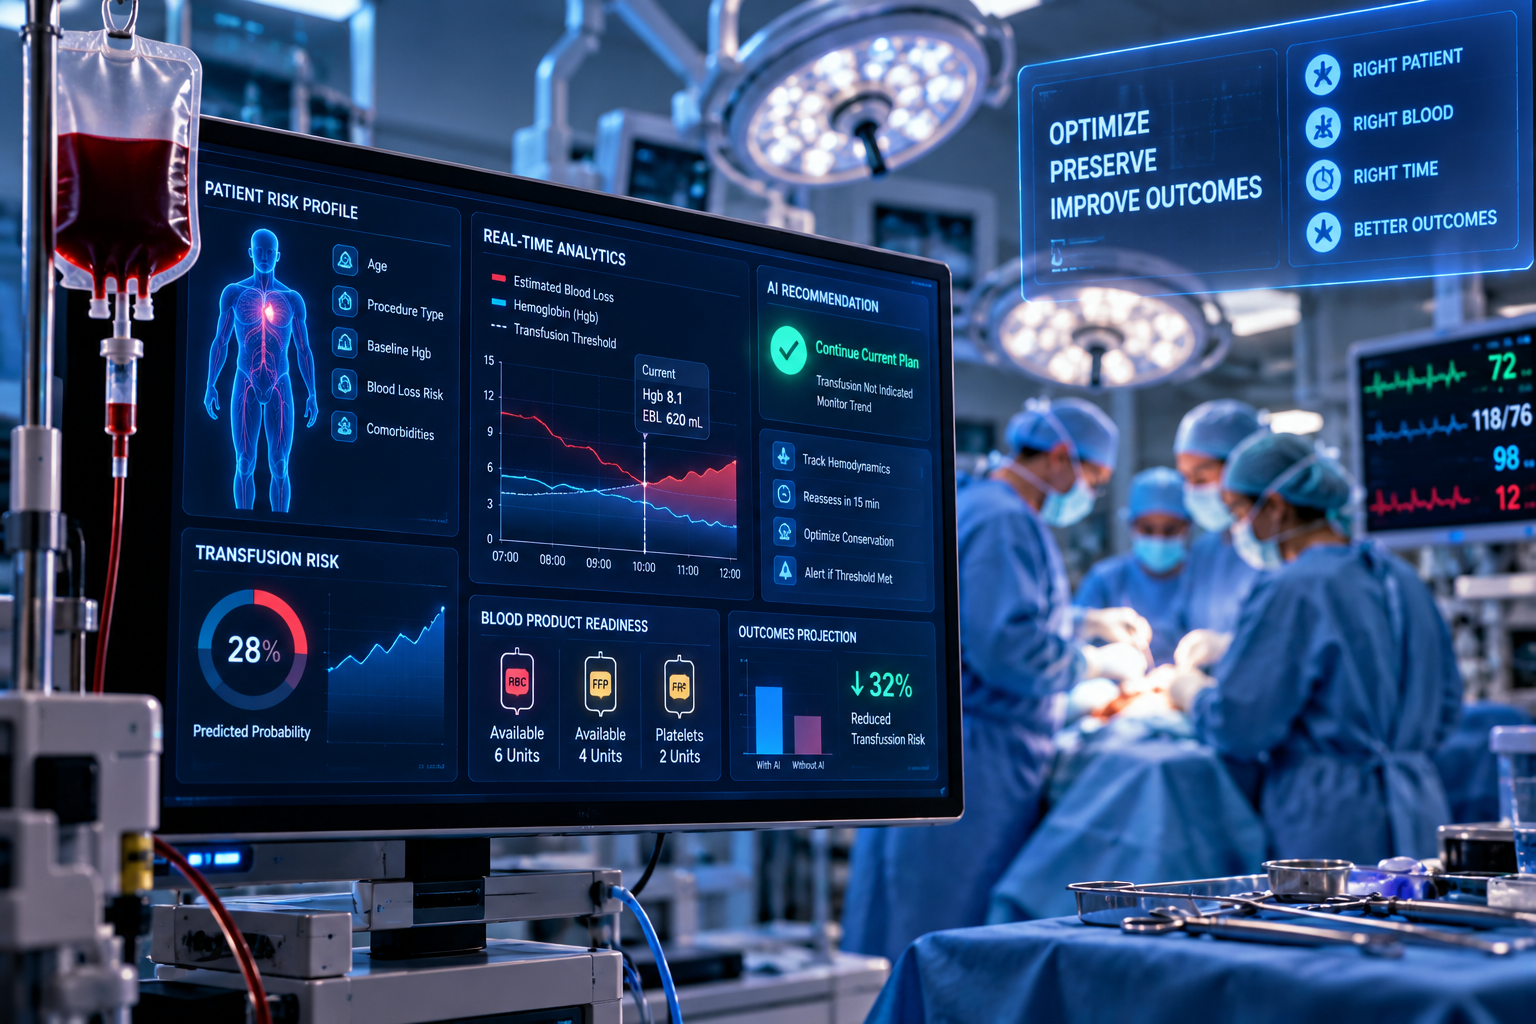
    To optimize patient safety and blood product utilization, health systems are implementing Real-Time Perioperative Blood Management Engines connected directly to OR Telemetry and Anesthesia Workstations. By continuously analyzing streaming physiological metrics, hemoglobin monitoring, and suction canister volume sensors, these systems predict acute transfusion requirements well before critical blood loss occurs.

    Accelerating Intraoperative Blood Management: Delayed Lab Testing vs. Real-Time Analytics

    Predictive analytics replace reactive lab waiting periods with continuous risk evaluation.

    [Streaming Anesthesia Telemetry & Optical Suction Sensors]

                               │

                               ▼

       [GoLiveX Real-Time Blood Management Engine]

                               │

        (Calculates Hemorrhage Velocity & Viscosity Drift)

                               │

                               ▼

     [Predictive Blood Product Order Prompt Delivered to Blood Bank]

    Operational Comparison: Legacy Blood Management vs. Real-Time OR Analytics

    Clinical VectorTraditional Intraoperative ProtocolGoLiveX Real-Time Perioperative Engine
    Hemorrhage DetectionReactive; based on visual estimates and delayed lab results.Predictive; continuously tracks vital trends, pulse co-oximetry, and sensor data.
    Data CollectionIntermittent laboratory blood draws every 30 to 60 minutes.Continuous real-time streaming of physiological metrics and fluid loss velocity.
    Blood Bank CoordinationManual phone calls after active bleeding is visually confirmed.Automated alerts notify blood banks ahead of time to prepare specific blood components.
    Transfusion PrecisionHigh risk of over-transfusion or delayed resuscitation.Targeted; algorithms recommend exact component ratios based on real-time deficit models.

    Primary Strategic Benefits for Surgical Services and Blood Banks

    1. Early Hemorrhage Alerting: Advanced velocity algorithms detect subtle, combined shifts in pulse pressure variation, continuous hemoglobin monitoring, and heart rate before systemic hypotension presents.
    2. Reduction in Donor Blood Waste: Accurately predicting actual transfusion needs prevents premature thaw and expiration of plasma and platelet units in the operating room.
    3. Automated Patient Blood Management (PBM) Compliance: Integrated decision support ensures intraoperative transfusions strictly adhere to evidence-based clinical practice guidelines.

    Key Takeaways

    • The Transfusion Race: Overcoming lab turnaround delays is critical during rapid intraoperative hemorrhage events.
    • Continuous OR Telemetry: Streaming sensor data surfaces early blood loss trends long before standard blood pressure drops occur.
    • Optimized Blood Bank Supply: Automated notification protocols streamline blood preparation and reduce wastage of vital donor units.
    • Improved Surgical Survival: Early, targeted transfusion guidance minimizes tissue ischemia and reduces post-operative surgical complications.

    To learn more about how organizations govern AI deployments securely, watch this video on AI trends and governance models for enterprise software.

    This video provides an expert overview of AI governance and operational frameworks that help companies implement secure, auditable, and resilient automation strategies.

  • Real-Time Sepsis Alerting & Hemodynamic Stability Tracking: Reducing Mortality in Critical Care

    Real-Time Sepsis Alerting & Hemodynamic Stability Tracking: Reducing Mortality in Critical Care

    In critical care management, septic shock represents one of the most volatile and time-sensitive clinical emergencies. While early sepsis identification focuses on antimicrobial administration, patient survival during severe progression hinges on hemodynamic stability—maintaining adequate organ perfusion pressure through precise fluid management and vasopressor titration.

    Traditionally, monitoring cardiovascular stability relies on periodic manual blood pressure measurements and sporadic mean arterial pressure (MAP) spot-checks. However, microvascular perfusion can deteriorate significantly before overt, systemic hypotension appears on standard bedside monitors. Relying on reactive measurements often delays life-saving adjustments to vasopressor infusions.

    To protect high-risk ICU patients, health systems are deploying Real-Time Hemodynamic Tracking Engines inside Bedside Telemetry Networks. By continuously analyzing high-frequency arterial line waveforms, heart rate variability, and lactate trends, these systems flag early vascular collapse hours before clinical decompensation occurs.

    Closing the Hemodynamic Window: Spot-Check Monitoring vs. Continuous Analytics

    Continuous tracking converts intermittent vital signs into a continuous, predictive trend line for clinical care teams.

    [Streaming Arterial Waveforms & Sensor Telemetry]

                            │

                            ▼

       [GoLiveX Real-Time Hemodynamic Engine]

                            │

       (Detects Subtle Vascular Resistance Shifts)

                            │

                            ▼

    [Instant ICU Bedside Alert & Vasopressor Titration Prompt]

    Operational Comparison: Traditional Monitoring vs. Continuous Hemodynamic Tracking

    Clinical ParameterTraditional Periodic Vital ChecksGoLiveX Continuous Hemodynamic Analytics
    Data CaptureDiscrete vital sign inputs logged at hourly nurse intervals.Continuous streaming evaluation of high-frequency arterial waveforms.
    Decompensation DetectionReactive; alerts after systemic blood pressure drops below threshold.Predictive; detects subtle stroke-volume variation and early vascular tone decay.
    Fluid ManagementGeneral fluid bolus administration based on static central venous pressure.Dynamic fluid responsiveness calculation guiding targeted, patient-specific fluid delivery.
    Vasopressor TitrationManual titration adjustments following post-event hypotensive episodes.Proactive bedside prompts recommending precise dosage adjustments to maintain MAP goals.

    Key Strategic Benefits for Intensive Care Teams

    1. Early Prediction of Septic Shock: Advanced waveform analysis detects early degradation in systemic vascular resistance, alerting clinicians before overt organ hypoperfusion occurs.
    2. Optimized Fluid Resuscitation: Continuous assessment of stroke volume variation prevents both under-resuscitation (leading to persistent tissue hypoxia) and fluid overload (causing pulmonary edema).
    3. Automated Nursing Decision Support: Integrated clinical decision tools surface clear, protocol-aligned recommendations for vasopressor titration directly at the patient’s bedside monitor.

    Key Takeaways

    • The Perfusion Race: Preventing tissue hypoperfusion during septic shock requires continuous, proactive cardiovascular oversight.
    • Waveform-Level Analytics: Evaluating high-frequency telemetry streams surfaces early vascular collapse long before standard blood pressure drops occur.
    • Precision Fluid Guidance: Dynamic physiological indicators ensure fluid delivery matches actual patient responsiveness, reducing pulmonary complications.
    • Streamlined Nursing Action: Bedside decision support aids rapid, confident vasopressor titration during critical care transitions.
  • Real-Time Pharmacy Prior Authorization: Eliminating Medication Delays at the Point of Care

    Real-Time Pharmacy Prior Authorization: Eliminating Medication Delays at the Point of Care

    Securing health plan coverage for specialized or high-cost medications remains one of the most frustrating administrative bottlenecks in clinical outpatient care. When a prescription requires prior authorization (PA), traditional workflows require nurses and clinical staff to complete lengthy forms, fax clinical documentation to payers, and await manual review.

    This manual friction creates severe care barriers. Patients frequently face multi-week delays before receiving critical therapies, leading to high rates of prescription abandonment and worsening clinical outcomes. Furthermore, clinical staff spend dozens of hours weekly tracking down coverage criteria instead of delivering direct patient care.

    To streamline prescription fulfillment, health networks are implementing Real-Time Pharmacy Prior Authorization Engines directly within EHR Order Workflows. By automatically matching patient clinical records against payer coverage rules, these systems secure medication approvals the moment a physician writes the prescription.

    Accelerating Prescriptions: Manual Prior Auth vs. Automated EHR Approval

    Real-time prior authorization unifies clinical documentation, coverage verification, and approval submission into a single point-of-care step.

    [Physician Orders Specialty Medication in EHR]

                            │

                            ▼

        [GoLiveX Real-Time Prior Auth Engine]

                            │

      (Extracts Required Clinical Criteria & Labs)

                            │

                            ▼

       [Direct Electronic Payer Rule Engine Check]

                            │

                            ▼

    [Instant Electronic Coverage Approval Delivered to Pharmacy]

    Operational Comparison: Legacy Manual PA vs. Real-Time EHR Automation

    Workflow VectorTraditional Manual Prior AuthorizationGoLiveX Real-Time Prior Auth Platform
    Data CollectionManual chart digging by clinical staff to find lab values and prior trial therapies.Automated extraction of diagnostic histories, lab results, and clinical notes from the EHR.
    Submission ChannelFaxes, phone calls, or external payer portal manual entries.Direct electronic data interchange (EDI/API) submission inside order workflows.
    Approval TimelineDays to weeks of waiting time; high risk of lost documentation.Seconds to minutes; real-time automated approvals at the point of prescribing.
    Medication AdherenceLow; high rate of patient prescription abandonment due to long delays.High; patients pick up approved medications without prolonged care interruptions.

    Primary Strategic Benefits for Healthcare Providers

    1. Instant Clinical Criteria Matching: The system evaluates relevant patient data—such as specific biomarker results or step-therapy history—against payer rules before the prescription order is finalized.
    2. Reduction in Staff Administrative Burden: Automating routine coverage approvals frees nurses and medical assistants from manual paperwork, allowing them to focus on direct care coordination.
    3. Alternative Drug Suggestions: If a requested medication is denied or requires extensive manual review, the platform instantly suggests covered, clinically equivalent formulary alternatives.

    Key Takeaways

    • The Prior Auth Barrier: Manual coverage approvals delay critical patient treatments and increase prescription abandonment rates.
    • Point-of-Care Integration: Generating prior authorization requests inside the EHR order screen streamlines coverage verification.
    • Automated Clinical Extraction: Advanced NLP pulls relevant lab results and clinical histories, fulfilling payer criteria automatically.
    • Improved Care Adherence: Accelerating approval timelines ensures patients receive necessary therapies without administrative delays.